
Breast cancer remains one of the most formidable health challenges confronting women globally, instilling widespread fear and uncertainty upon diagnosis. However, advancements in modern oncology and diagnostic technologies have transformed the medical outlook for millions. A cancer diagnosis is no longer an inevitable harbinger of despair; rather, it marks the beginning of a medical journey where recovery is increasingly achievable, particularly when addressed in its nascent stages. The fundamental question of whether breast cancer can be cured yields an encouraging, albeit nuanced, affirmative response. Medical experts emphasize that survival and complete remission are heavily contingent upon a constellation of clinical factors, with the stage of the disease at the time of initial detection serving as the most critical determinant.
The Clinical Reality of Breast Cancer Recovery and Staging
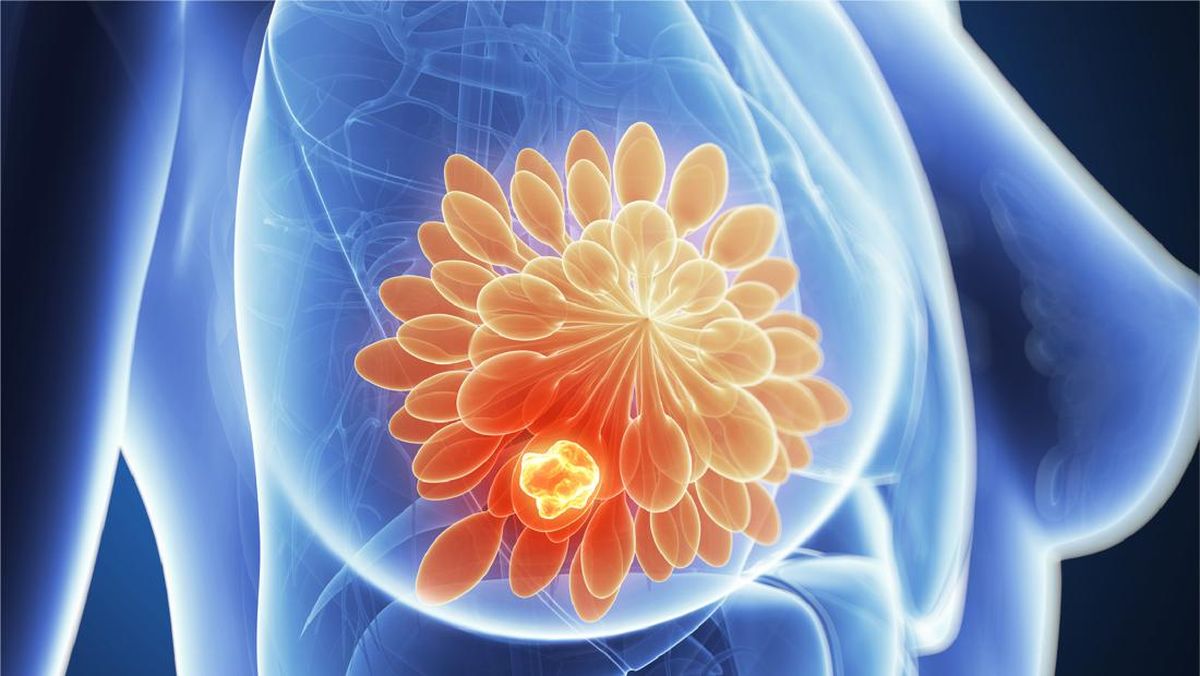
At the core of oncology is the principle of staging, which categorizes how far a cancer has spread throughout the body. When breast cancer is identified in its earliest stages—often referred to as Stage 0 or Stage I—the malignant cells remain localized primarily within the breast tissue and have not infiltrated surrounding lymph nodes or distant organs. In such optimal scenarios, the efficacy of medical intervention reaches its peak, affording patients significantly higher rates of long-term survival and successful eradication of the disease.
Dr. Sonar Soni Panigoro, an esteemed oncology consultant surgeon at Eka Hospital BSD, underscores the profound impact of prompt medical intervention. According to Dr. Sonar, recognizing bodily changes from the outset empowers medical professionals to formulate precise, individualized diagnostic and therapeutic strategies. Intervening during the early phases of tumor development not only maximizes the probability of clinical success but also preserves the patient’s overall well-being by potentially sparing them from more aggressive, systemic treatments required in advanced stages. Consequently, health authorities persistently advocate for heightened bodily awareness among women, urging them to bypass hesitation and seek professional medical evaluations whenever anomalous physical shifts occur.
The clinical narrative shifts when the disease progresses to advanced stages—such as Stage III or Stage IV, where metastasis allows cancer cells to migrate to vital organs including the bones, liver, lungs, or brain. While completely curing metastatic breast cancer presents profound medical complexities, contemporary therapeutic protocols are remarkably sophisticated. Modern oncology shifts its focus toward disease management, halting or slowing cellular proliferation, alleviating distressing symptoms, and significantly enhancing the patient’s quality of life. Modern therapeutic arsenals are multifaceted, encompassing surgical interventions—ranging from lumpectomies to mastectomies—alongside adjuvant and neoadjuvant therapies such as chemotherapy, radiation therapy, hormone receptor therapy, targeted biological therapies, and immunotherapy. The orchestration of these treatments is meticulously tailored to the unique molecular subtypes and genetic markers of the tumor, ensuring a personalized approach to patient care.
Identifying Subtle Warning Signs: Symptoms Every Woman Must Know
Empowering women with accurate medical knowledge begins with symptom recognition. Detecting early physiological anomalies can dramatically alter the trajectory of a patient’s health. Medical professionals advise vigilance regarding several hallmark physical indicators associated with breast abnormalities:
- The sudden appearance of distinct lumps or thickening within the breast tissue or underarm (axillary) region.
- Visible or tactile alterations in the skin of the breast, such as dimpling, puckering, or areas that appear pulled inward.
- Spontaneous shifts in the overall symmetry, size, or contour of the breast, alongside unexplained inversions or directional changes of the nipple.
- Nipple discharge that occurs without expression, particularly if the fluid is bloody, clear, or persistent.
- Unexplained rashes, persistent scaling, or textural changes localized around the nipple or areola.
- Dermal thickening or an orange-peel texture (known medically as peau d’orange), which indicates lymphatic blockage within the skin.
Crucially, medical specialists caution against the dangerous misconception that all lumps or abnormalities are benign simply because they are painless. In its primary developmental stages, breast cancer rarely induces physical pain or discomfort. Therefore, the absence of pain must never be utilized as a rationale for postponing clinical evaluations. Any novel or persistent anomaly warrants a thorough diagnostic assessment by qualified healthcare providers to definitively rule out malignancy or initiate timely therapeutic protocols.
The Evolution of Screening and Diagnostic Protocols
Beyond symptom vigilance, structured medical screening forms the bedrock of preventive oncology. Dr. Sonar highlights that comprehensive health evaluations and proactive physician consultations must be calibrated according to individual risk profiles, age brackets, and personal or familial medical histories. While self-examinations are invaluable for fostering intimate familiarity with one’s own anatomy, clinicians stress that self-checks serve merely as a preliminary awareness tool and cannot substitute for professional diagnostic screenings.
For average-risk women, standardized guidelines often recommend routine mammographic screenings beginning at specific age milestones, supplemented by ultrasound evaluations when dense breast tissue obscures clarity. When diagnostic imaging reveals suspicious lesions or structural anomalies, physicians typically escalate the investigative process to a tissue biopsy. Pathological analysis of the biopsy sample remains the undisputed gold standard for confirming a diagnosis, identifying hormone receptor status (such as Estrogen Receptor, Progesterone Receptor, and HER2/neu status), and guiding oncologists toward the most efficacious therapeutic regimen.
Furthermore, women harboring a documented family history of breast or ovarian malignancies—particularly those carrying inherited mutations in the BRCA1 or BRCA2 genes—face elevated lifetime risks. For these high-risk cohorts, standard screening timelines are frequently accelerated and supplemented with advanced diagnostic modalities, such as Magnetic Resonance Imaging (MRI), alongside genetic counseling.
Global Epidemiological Context and Public Health Implications
The imperative for early detection extends far beyond individual clinical encounters; it represents a monumental public health priority on a global scale. According to data compiled by the World Health Organization (WHO) and the International Agency for Research on Cancer (IARC), breast cancer stands as the most frequently diagnosed cancer among women worldwide, accounting for millions of new cases annually. The socioeconomic burden of this disease is staggering, affecting not only the health systems of high-income nations but increasingly straining healthcare infrastructure in low- and middle-income countries where late-stage presentation remains distressingly prevalent.
Epidemiological analyses consistently demonstrate a stark survival disparity dictated by the stage at diagnosis. In nations equipped with robust, population-wide screening programs and unhindered access to advanced oncological care, five-year survival rates for localized breast cancer exceed ninety percent. Conversely, in regions constrained by diagnostic delays, lack of public awareness, or financial barriers to healthcare access, survival rates drop precipitously due to late-stage diagnoses. This geographical and socioeconomic divide underscores the critical necessity of sustained public health campaigns focused on education, destigmatization, and the decentralization of diagnostic facilities.
Chronology of Modern Breast Oncology Milestones
The current landscape of breast cancer care is the product of decades of relentless scientific inquiry, clinical trials, and paradigm shifts in surgical and medical oncology. Tracing the historical evolution of breast cancer management highlights the remarkable strides achieved by the medical community:
- Late 19th to Mid-20th Century: The era dominated by the radical mastectomy pioneered by Dr. William Halsted, which involved the extensive removal of the breast, underlying chest muscles, and regional lymph nodes. While revolutionary for its time, it frequently resulted in severe physical morbidity.
- 1970s to 1980s: Landmark clinical trials led by researchers like Bernard Fisher demonstrated that lumpectomy combined with radiation therapy yielded survival rates equivalent to radical mastectomy, ushering in modern breast-conserving surgery and preserving patient quality of life.
- 1990s: The advent of targeted therapy with the introduction of trastuzumab (Herceptin), revolutionizing the treatment of HER2-positive breast cancer by precisely attacking specific molecular pathways rather than broadly destroying dividing cells through chemotherapy alone.
- 2000s to Present: The genomic revolution in oncology, characterized by gene expression profiling (such as Oncotype DX and MammaPrint), which allows clinicians to predict recurrence risks and tailor chemotherapy regimens precisely, sparing countless patients from unnecessary toxic treatments. Additionally, immunotherapy and antibody-drug conjugates have continuously expanded the therapeutic horizon for advanced and triple-negative breast cancer subtypes.
Broader Impact and Economic Implications
The societal implications of optimizing breast cancer outcomes ripple across familial, economic, and institutional domains. Because breast cancer frequently strikes women in their prime working and caregiving years—spanning decades of professional and domestic contributions—delayed diagnoses exact a heavy economic toll through lost productivity, extensive medical expenditures, and long-term disability.
Investing in comprehensive breast health infrastructure—ranging from community-level educational initiatives to state-of-the-art radiological centers—yields profound dividends. Public health economists note that robust early detection programs drastically reduce downstream expenditures associated with managing advanced, metastatic disease, which requires prolonged, highly expensive multi-agent systemic therapies and palliative care.
Ultimately, navigating the complexities of breast cancer requires a synchronized alliance between proactive individuals, primary care physicians, specialized oncologists, and health policymakers. By dismantling barriers to screening, fostering open dialogue regarding physical health, and embracing the realities of early detection, society can steadily diminish the morbidity and mortality associated with this pervasive disease. While a universal, fail-safe cure remains an ongoing frontier of medical research, the existing arsenal of diagnostics and therapies offers profound hope: when intercepted early, breast cancer is a formidable adversary that can be successfully confronted, managed, and overcome.



















